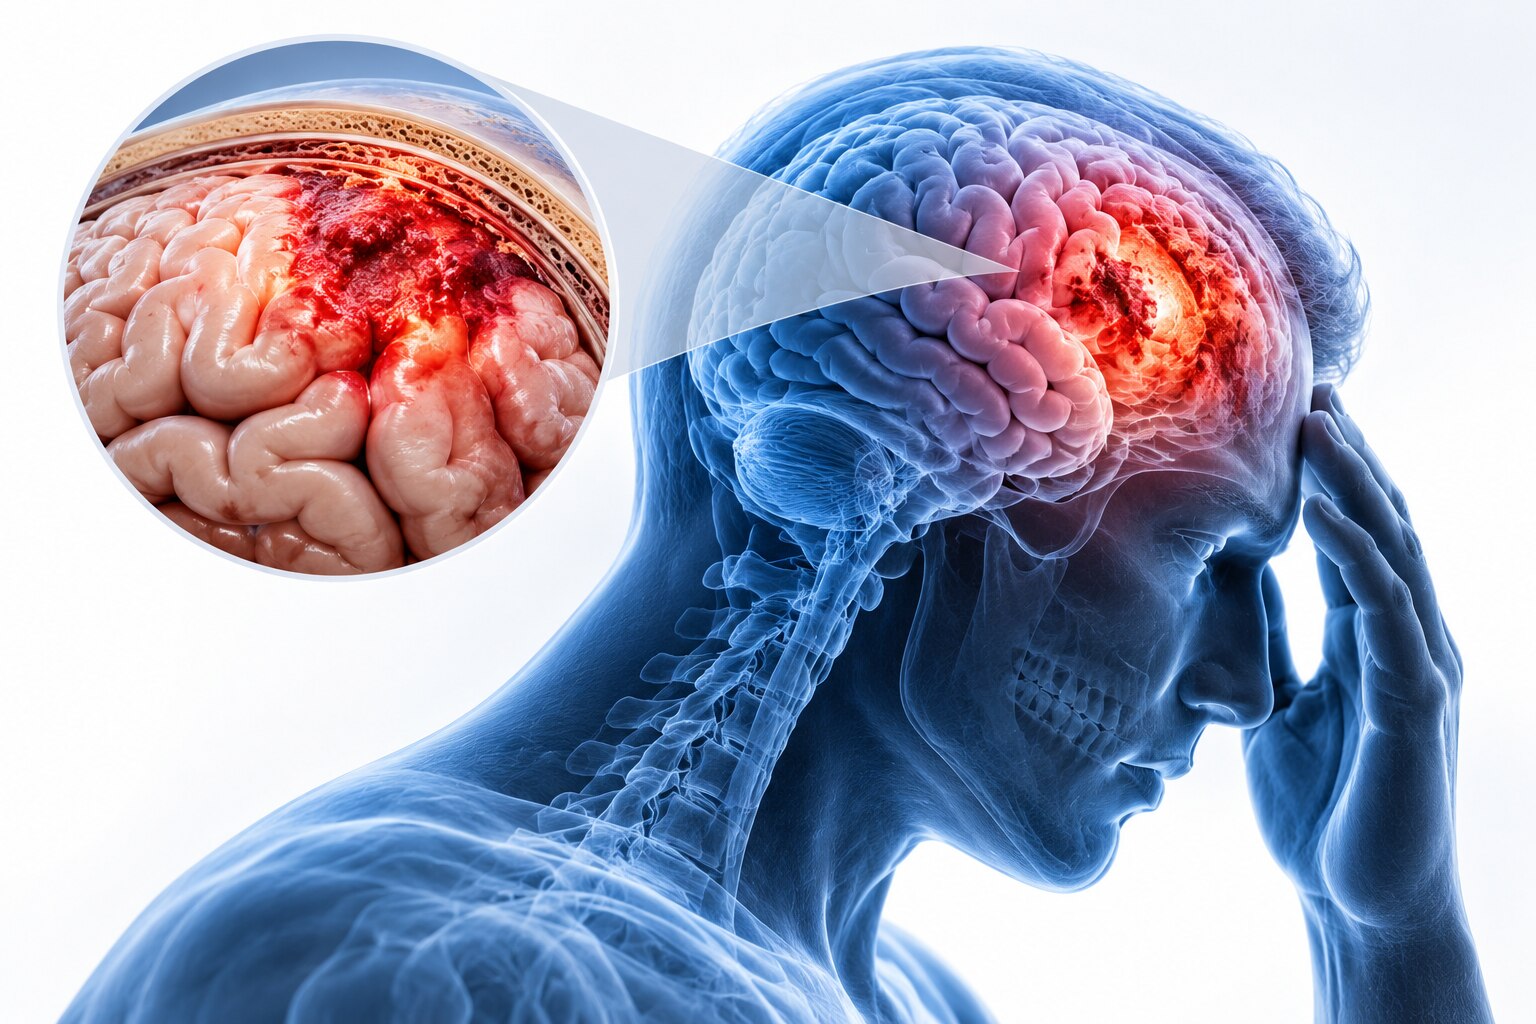
Treatment begins with a time-sensitive decision: does the patient need resuscitation and immediate transfer to a neurosurgical centre, or can doctors safely observe and investigate further? By the end, you will understand how the examination, CT findings, injury timing and patient factors determine observation, ICU care, minimally invasive treatment or open surgery.
Key takeaways
- Transfer suspected TBI immediately to a centre with CT, ICU and neurosurgical cover.
- Surgeons combine neurological examination, CT findings and clinical deterioration when choosing surgery.
- Observation is safer when the injury is stable and the patient can receive close monitoring.
- Tell the team about blood thinners, age, medical conditions and injuries elsewhere.
The first decision is emergency transfer, not elective surgery
Immediate transfer is required when a head injury could worsen before an elective appointment: take the patient to a Mumbai centre with 24-hour CT, neurosurgical assessment, ICU monitoring, blood products and an operating theatre. The first decision is safe stabilisation and rapid imaging, not booking surgery.
Call emergency services or arrange monitored transfer after any of these warning signs:
- Falling consciousness, confusion or a Glasgow Coma Scale score that is decreasing
- One pupil larger than the other, a new weakness, speech trouble or loss of coordination
- Repeated vomiting, a seizure, severe or worsening headache, or unusual drowsiness
- Clear fluid or blood from the nose or ear, an open or depressed skull wound, or loss of consciousness after a major impact
- Use of warfarin, apixaban, rivaroxaban, aspirin or another antiplatelet drug, especially with a new headache or neurological change
A CT scan is usually the urgent first test because it quickly shows bleeding, swelling, skull fracture and pressure effects. MRI can wait when the patient is unstable; moving them for it can delay resuscitation or evacuation of a CT-visible haematoma.
This answers how is traumatic brain for injury surgery chosen in Mumbai: examination, CT and deterioration guide urgency. A traumatic brain injury neurosurgeon in Mumbai may recommend observation rather than surgery when both the scan and examination remain stable.
How the examination and CT scan determine whether surgery is needed
Surgery becomes more likely when the neurological examination shows pressure or deterioration and the CT shows a sizeable, expanding or space-occupying lesion. A falling Glasgow Coma Scale score, unequal or newly non-reactive pupils, worsening weakness, repeated vomiting or seizure raises concern, especially alongside midline shift or compressed basal cisterns.
Headache alone does not establish a need for an operation.
| Finding | CT measurement or feature | Likely surgical purpose |
|---|---|---|
| Epidural haematoma | Volume over 30 cm³, or deterioration, coma or an abnormal pupil | Evacuate the clot |
| Acute subdural haematoma | Thickness over 10 mm or midline shift over 5 mm, regardless of GCS | Evacuate the clot |
| Contusion or swelling | Large frontal or temporal contusion, expanding haemorrhage, compressed cisterns or significant shift | Evacuate or decompress |
| Depressed skull fracture | Fragment depressed below the inner skull table, with dural tear, contamination, exposed brain or an underlying haematoma | Elevate or repair the fracture |
These figures guide TBI surgery treatment decisions; they do not replace the examination or scan trend. A smaller haematoma can still require urgent treatment if consciousness falls, a pupil changes or repeat CT shows enlargement. A stable scan with a stable examination supports observation and repeat CT instead.
Decompressive craniectomy removes part of the skull to relieve persistent intracranial pressure after other measures fail. It can reduce death in selected severe injuries but may leave survivors with profound disability, so the brain injury operation evaluation must address both outcomes.
When observation, medication or ICU monitoring is safer than an operation
A small, stable haematoma or contusion is often safer to observe than to remove. Doctors admit the patient for repeated pupil and consciousness checks, follow-up CT, head elevation, pain and vomiting control, seizure treatment when indicated, and careful oxygen and blood-pressure support. A CT abnormality alone does not mandate craniotomy.
Observation becomes unsafe when:
- Consciousness falls, a pupil becomes unequal or unreactive, weakness appears, vomiting persists, or a seizure occurs.
- A repeat CT shows an enlarging haematoma, increasing midline shift, compressed basal cisterns or worsening swelling.
- An acute subdural haematoma exceeds 10 mm in thickness or shifts the brain more than 5 mm; smaller clots still need urgent treatment when coma, pupil abnormalities or raised pressure develop.
In severe TBI, ICU teams may place an intracranial-pressure monitor after resuscitation when the Glasgow Coma Scale is 3–8 and CT is abnormal. An ICP above 22 mmHg prompts treatment, interpreted with the examination, CT, cerebral perfusion pressure and duration of elevation—not as an automatic order for surgery.
MRI helps when the patient is stable but CT does not explain persistent neurological findings. It is not a reason to delay urgent evacuation. Avoid corticosteroids for traumatic brain swelling: high-dose methylprednisolone increased mortality in the CRASH trial.
These findings form the core of tbi surgery treatment decisions: protect brain function while avoiding an operation whose risks exceed its benefit.
How age, medicines and other injuries change the treatment plan
A child is not a small adult. Surgeons interpret the Glasgow Coma Scale against age, use paediatric drug and ventilation doses, and consider the child’s developing brain when choosing observation, evacuation or decompression.
A traumatic brain injury neurosurgeon in Mumbai will also check for an unsafe injury history when the explanation does not match the findings.
Older adults need a different risk calculation. Brain shrinkage can allow a subdural haematoma to expand before symptoms appear, while dementia, stroke or hearing loss can obscure a new decline. Frailty, heart and lung disease, baseline independence and the likely disability after surgery all affect whether aggressive treatment is worthwhile.
Tell the team the exact name, dose and last time taken for warfarin, apixaban, rivaroxaban, dabigatran, aspirin or clopidogrel. Reversal may be urgent, but anticoagulant use alone does not prove that craniotomy is needed; the scan and examination still decide.
- Low oxygen or low blood pressure requires immediate correction because secondary brain injury can worsen while the team evaluates the bleed.
- Multiple injuries change the order of treatment: airway control, chest bleeding, abdominal haemorrhage and a cervical-spine injury may need attention alongside the head injury.
- Dr. Anshu Warade can help families clarify how age, medication reversal, other injuries and expected recovery alter the proposed operation or monitoring plan.
Related services
Brain (Cranial) Surgeries 🧠 Brain (Cranial) Surgeries by Dr. Anshu Warade Brain (Cranial) Surgeries involve advanced surgical procedures to treat conditions affecting the... View service → |
Neurological Examination 🧠 Neurological Examination by Dr. Anshu Warade A Neurological Examination is a detailed clinical assessment used to evaluate the functioning of the... View service → |
What families should ask before and after a TBI treatment decision
Give the team a precise timeline and baseline: the injury mechanism, loss of consciousness, vomiting, seizure, new weakness, alcohol or drug use, previous neurological problems, anticoagulants, allergies, last meal and other injuries. This information sharpens the brain injury operation evaluation and prevents avoidable delays.
- Which CT finding is the procedure intended to correct: an epidural or subdural haematoma, contusion, depressed or contaminated fracture, dural tear, or swelling?
- What operation is proposed, when must it happen, and what examination or scan change would make observation unsafe?
- Is the alternative repeat CT, ICU monitoring, medication or a less-invasive procedure? What would trigger escalation?
- If decompressive craniectomy is discussed, what are the chances of survival with severe disability, and when would skull reconstruction occur?
- What is the plan for intracranial-pressure monitoring, repeat imaging, seizure prevention and rehabilitation?
| Option | What it means | Key trade-off to ask about |
|---|---|---|
| Observation | Neurological checks and repeat CT | Avoids surgery, but deterioration requires rapid action |
| Clot evacuation or fracture repair | Removes pressure or repairs damaged bone and dura | Treats a defined lesion but carries bleeding, infection and anaesthesia risks |
| Decompressive craniectomy | Temporarily removes skull to control resistant swelling | Can reduce mortality while increasing survival with severe disability |
Ask why steroids appear in the plan: high-dose methylprednisolone is not routine acute TBI treatment and increased mortality in the CRASH trial. After the decision, ask which warning signs require immediate review, who gives updates, and when the next CT and family meeting will occur.
Frequently asked questions
How is traumatic brain injury surgery chosen in Mumbai?
A neurosurgeon reviews the patient’s airway and circulation, neurological examination, CT scan, symptoms and signs of pressure or bleeding before recommending surgery, monitoring or observation.
When does a traumatic brain injury require emergency transfer?
Transfer immediately when a head injury could worsen before an elective appointment, especially if the patient has reduced consciousness, repeated vomiting, seizures, weakness or increasing confusion.
When is observation safer than a brain injury operation?
Observation is safer when the CT abnormality is stable, neurological findings remain reassuring and the patient can receive repeated examinations, vital-sign checks and follow-up imaging.
What should families ask before a TBI treatment decision?
Ask what the CT shows, whether the injury is worsening, why surgery or monitoring is recommended, what risks require immediate action and how recovery will be assessed.
Keywords